Evidence before treatment.
Testosterone replacement therapy is considered when compatible symptoms and clinical findings align with consistently low testosterone, confirmed through repeat morning fasting testing. A low result alone is not enough.

Testosterone evaluation alongside metabolic health, sleep and medical history. Confirmed findings come first. Treatment and monitoring follow when clinically indicated.

Testosterone replacement therapy is considered when compatible symptoms and clinical findings align with consistently low testosterone, confirmed through repeat morning fasting testing. A low result alone is not enough.
Weight, sleep disorders, medications and other health conditions can influence testosterone findings. Addressing reversible contributors may be the right first step; not every evaluation leads to TRT.
Treatment requires ongoing review of response, testosterone levels, blood counts and adverse effects, with prostate assessment when appropriate. Fertility goals and individual risks belong in the decision from the start.
Connected evaluation. Separate treatment decisions. TRT is not an automatic companion to weight-management or peptide care.
Delivery format follows evaluation—not the other way around. Explore how the clinical conversations differ.

Injectable testosterone is one delivery option considered after confirmed deficiency and an individual prescribing evaluation.
The provider confirms the exact formulation and approval status; compounded medications are not FDA-approved. TRT can suppress sperm production. Product-specific risks, monitoring and fertility considerations require review.
The label identifies a treatment format, not a particular dispensed formulation, strength or approval status. Packaging varies. FDA-approved and compounded formulations are distinct; compounded medications are not FDA-approved. Booking does not guarantee a prescription.

Creams and gels are another testosterone-care conversation. Suitability and precautions depend on the exact prescribed product.
FDA-approved products and compounded creams are distinct; compounded creams are not FDA-approved. Some topical testosterone products can transfer through contact. Product-specific precautions and fertility risks require review.
The pump is a generic format illustration, not clinic packaging or an approved product label. Compounded creams are not FDA-approved; approval or evidence for one formulation does not transfer to another. Availability and format-specific costs require confirmation.

Hormone pellets require an in-office procedure and an individual discussion of suitability, risks and alternatives.
Some pellet products are compounded and are not FDA-approved. The monthly testosterone program does not establish that every format or procedure is included. Medication and procedure costs must be confirmed.
The pictured objects do not represent a dose, specific ingredient, available inventory or recommended regimen. Some pellet products are compounded and are not FDA-approved. Testosterone-related monitoring and fertility considerations still apply.
Educational formats—not a bundle, product catalog or guaranteed prescription. Selection and availability are confirmed during an individual evaluation.
Published research helps explain the clinical conversation. It does not predict an individual result.
Baseline group median
During the 1-year study period
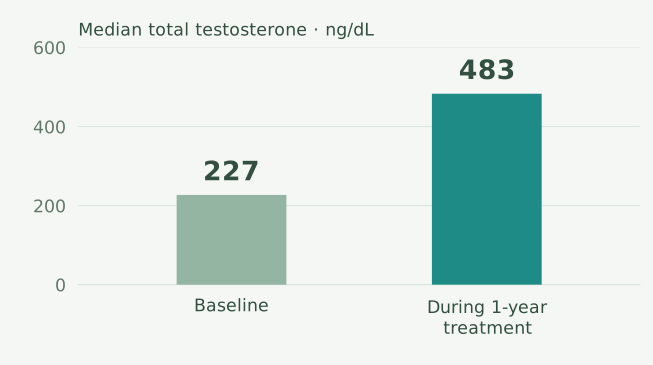
| Study category | Total testosterone |
|---|---|
| Baseline | 227 ng/dL |
| During 1-year treatment | 483 ng/dL |
A clearer view of the markers that may inform evaluation and follow-up.
Total testosterone below this level can support evaluation. It is not a standalone diagnosis or an optimal target. Compatible findings and repeat testing matter.
Total circulating testosterone, including bound and unbound hormone.
Supports evaluation alongside symptoms and repeat morning measurements; one low result is not a diagnosis.
Unbound testosterone, measured or calculated with validated methods.
May clarify borderline total testosterone or altered SHBG; not required in every evaluation.
Protein that binds testosterone and affects interpretation of total testosterone.
Helps interpret total and calculated free testosterone when binding levels differ.
Pituitary signals involved in testosterone production and sperm development.
When indicated, helps distinguish testicular causes from pituitary or hypothalamic causes.
Average blood glucose over approximately two to three months.
Helps assess diabetes risk and monitor glucose management; some blood conditions affect accuracy.
Cholesterol fractions and triglycerides in blood.
Adds cardiovascular risk context; goals depend on overall risk and clinical history.
Estimates fat and lean mass; not a blood test.
Shows weight composition beyond the scale; measurement conditions affect comparisons.
A blood marker reflecting growth-hormone activity, interpreted against age-based ranges.
For suspected growth-hormone disorders or treatment monitoring, not routine wellness screening; a result alone does not diagnose deficiency.
Blood cell counts and the red-cell proportion of blood.
Testosterone can raise hematocrit; baseline and follow-up testing help assess treatment safety.
A prostate-related blood marker; not a cancer diagnosis.
Prostate monitoring depends on age, risk, and shared decision-making; elevated results need clinical interpretation.
Symptoms, adverse effects, treatment response, and relevant health history.
Connects results with examination, medications, fertility plans, and safety; numbers alone do not determine treatment.
Examples, not a fixed panel. Test selection and timing depend on indication, age, risk, medications, and treatment. Reference ranges vary by assay. DXA and clinical review are not blood tests. AUA guidance ↗
Assessment, appropriate treatment and ongoing monitoring form the clinical foundation. Training and daily habits remain part of the wider conversation.
Self-pay. No insurance billing. HSA/FSA eligibility depends on the individual plan. The clinic confirms the complete cost before care begins.
View all pricingIncludes testosterone therapy if prescribed, monthly provider visits, review of follow-up labs and dose adjustments. The $49 first consultation and $50 initial in-office lab panel are separate. Follow-up, additional and repeat lab fees are separate; route-specific and pellet costs require confirmation.
Book NowReview medical history, relevant concerns, medications, metabolic health, sleep and reproductive plans.
Use appropriate laboratory testing and assess potential causes before deciding whether treatment is indicated.
When TRT is appropriate, establish monitoring and revisit benefits, tolerability and the continuing need for treatment.
Context matters. These answers explain the care approach, not an individual treatment recommendation.
No. Diagnosis requires compatible clinical findings and repeat testing. Reversible causes and other explanations must also be considered.
TRT can suppress sperm production. Current or future fertility plans may change the treatment pathway and warrant specialist input.
These factors can affect the clinical picture. Weight loss can improve obesity-related testosterone reductions in some men, while sleep-disorder assessment may identify a separate care need.
Houston clinic. Texas telehealth.